Biceps Tenodesis
Surgery for Biceps Tendinosis/Tendinopathy
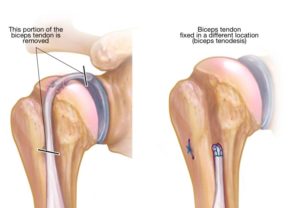
What is biceps tenodesis?
Biceps tenodesis is a surgery performed to alleviate the pain caused by biceps tendinosis. Arthroscopic surgery is a minimally invasive procedure where surgery is performed via a ‘keyhole’ approach through two or three small incisions using a piece of equipment which is a bit like a thin telescope (an arthroscope).
Do I need to have this bicep surgery?
Biceps Tendonitis will usually resolve within one year. If the pain persists and is generally not relieved with time or cortisone injections, then a patient may consider surgery since it’s likely there are more problems in the shoulder. There is usually no rush on surgery. Until conservative measures are no longer providing a patient with adequate pain relief, particularly if a person is having trouble sleeping, getting dressed, doing their job or preventing them from doing what they want to do, then surgery is usually recommended. This procedure is recommended for patients who have partial or full-thickness biceps tendon tears, biceps instability, SLAP lesions, or biceps tendinopathy. Read more about biceps tendinitis here.
What happens during the bicep tenodesis surgery?
During your surgery you are generally sat up in a beach chair type position. The operation is usually done via keyhole surgery (arthroscopy). The surgeon introduces a camera into your shoulder through a small incision and watches the images on a TV screen. Photos are taken of the findings. Here is the
Biceps tenodesis is a procedure during which the surgeon cuts the attachment of the biceps tendon to the labrum (cartilage around shoulder socket) and reattaches it to the humerus (upper arm bone). The benefit of reattaching the tendon below the bicipital groove is restored function and decreased pain. Removing the painful part of the biceps usually resolves symptoms and restores normal function. After the surgery, the small wound is closed using stitches. For more detailed information, you can read Tenodesis: Procedure, Recovery, and Outcomes
Watch: Shoulder Pain When Throwing? Biceps Tendonitis Explained
Understanding the difference between biceps tendon irritation, instability, and tear can help you recognize why you’re feeling pain during rotation or throwing — watch the video below for a clear, expert explanation.
Will I feel any pain in my bicep?
Your arm will feel numb because of the nerve block/local anesthetic used during your operation, but this should wear off during the first 24 hours after the operation. Post-operative pain is normal, and you will receive medication to help minimize this pain.
What are the risks of surgery failure?
As with any surgery, shoulder arthroscopy carries some risk, however, it has been shown to be safe with few complications.
Arthroscopic biceps tenodesis is routinely performed and is generally a very safe procedure. Before suggesting the operation, your doctor will have considered that the benefits of the procedure outweigh any disadvantages. However, to make an informed decision and give your consent, you need to be aware of the possible side effects and complications associated with most surgical operations.
Sugery Complications may include:
- Infection – this is a very serious complication and significant measures are taken to avoid it, for example you will be given antibiotics to try to guard against it.
- Nerve injury – the risk of this is very rare, but if damage occurs further treatment or surgery may be needed.
- Bleeding – this is rarely an issue as arthroscopic capsular release is a ‘keyhole’ procedure with very little blood loss.
- Thrombosis/blood clot – this is rarely an issue in shoulder surgery.
- Symptoms of stiffness may return – this is unusual, but it may become necessary to repeat the operation if the stiffness is troublesome.
Frequently Asked Questions about Biceps Surgery
1. How do I know if my shoulder pain is coming from the biceps tendon?
Biceps tendon pain is usually felt at the front of the shoulder and often travels down the upper arm. It tends to flare with overhead reaching, rotation of the shoulder (think ‘reach in the back seat of the car to grab a bag and pull it forward, reaching behind to put a coat on, tucking your pants in), and throwing, and many patients report pain that wakes them at night when lying on that side.
2. Do I need surgery for a torn or ruptured biceps tendon?
Not always. A proximal biceps tendon rupture at the shoulder often settles on its own, and many patients retain good function with little measurable strength loss. Non-surgical management is reasonable when pain resolves. Surgery is considered when pain persists, when cramping or fatigue limits activity, when the cosmetic deformity is unacceptable, or when the biceps problem accompanies a rotator cuff or labral tear that needs treatment anyway.
3. Where is the incision, and will biceps surgery leave a visible scar?
Dr. Gobezie commonly uses a subpectoral approach, placing a small incision in the fold below the armpit where the pectoral muscle meets the arm. The position hides the scar well, and most patients find it difficult to see once it has matured. Arthroscopic portals used during the same procedure are a few millimeters across and typically fade to faint marks.
4. How long is recovery after biceps surgery?
A sling is generally worn for 2 days following a “no sling” technique for postoperative rehabilitation. It is important to follow the activity guidelines we provide to our patients in order to protect the tendon-to-bone healing. Most patients doing desk-based work return within one to two weeks, still wearing the sling. Progressive strengthening begins once healing is confirmed, and return to sport and unrestricted lifting typically falls between three to six months. Strength continues to improve for several months beyond that.
7. When can I drive and return to work after biceps surgery?
Driving typically resumes by 1 week after surgery once you are out of the sling for daily activity, off narcotic pain medication, and able to control the wheel comfortably with both hands. For most patients, this is around four to six weeks. Return to work depends on the physical demands of the job. Sedentary work is often possible within one to two weeks, while jobs involving lifting, overhead reaching, or repetitive use of the arm generally wait until strengthening is well underway. Dr. Gobezie sets individual restrictions at your follow-up visits.